Nasal antibodies cut Omicron reinfection risk when blood defenses fall short
Vaccines protect the bloodstream, but immune guards stationed inside the nose are what actually prevent respiratory viruses from establishing an infection, according to new research tracking healthcare workers.

A person can receive multiple vaccine doses, show abundant circulating antibodies in laboratory blood tests, and still test positive for a respiratory virus a short time later. Standard injected vaccines deliver their payload into muscle tissue, training the immune system to deploy defenses that circulate widely through the bloodstream. While those circulating proteins reliably protect the lungs and other internal organs against severe injury, they do not stand sentry at the physical threshold where airborne pathogens first land.
Understanding what stops an initial infection matters because blood-based immunity alone has not halted transmission as new viral variants emerge. Halting transmission requires stopping the pathogen at the doorway rather than fighting it after it has breached host tissues. Deciphering the exact biological barriers that block infection helps explain how an uncontrolled pandemic gradually transitions into a lower-level, endemic circulation of respiratory illness.
The biological sequence of a respiratory viral infection follows a clear, stepwise chain of events. A person breathes in airborne droplets containing viral particles through the nose or throat. To establish a productive infection, those particles must bind to receptors on the delicate surface cells of the mucosal lining. If protective proteins are stationed directly on that wet mucosal surface, they can latch onto the virus immediately and neutralize it before it penetrates the tissue. If surface defenses are sparse, the virus penetrates the mucosal cells, multiplies, and spreads into adjacent tissue, which eventually summons circulating antibodies from the bloodstream to clean up the infection and protect deeper organs.
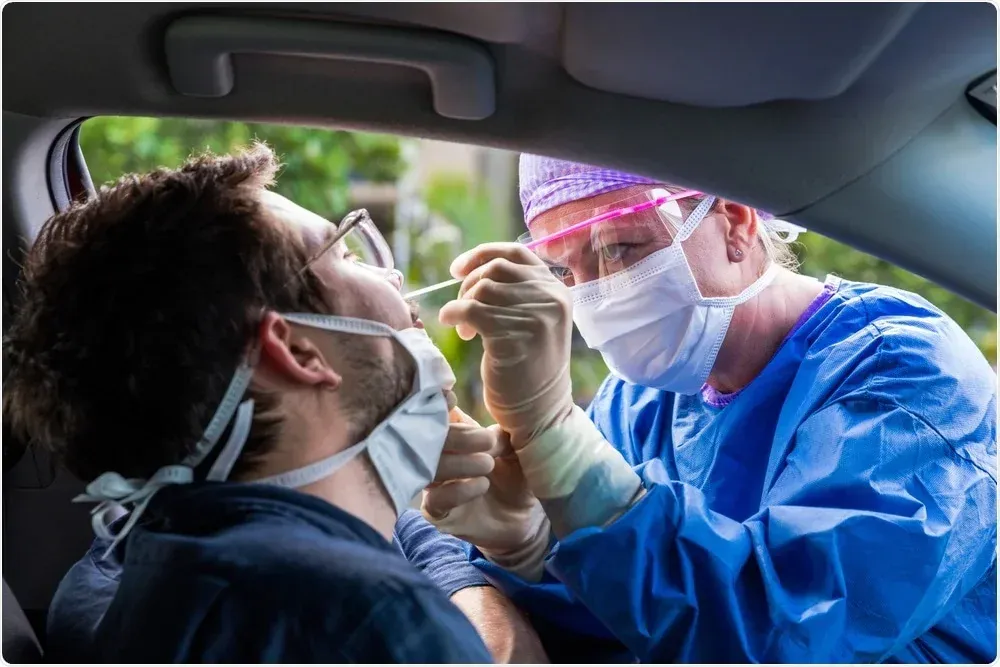
A doctoral research thesis examining four linked investigation cohorts has now documented the precise division of labor between systemic blood antibodies and mucosal surface defenses.1 The studies followed cohorts of vaccinated healthcare workers to evaluate how circulating immunoglobulin G and nasal immunoglobulin A protect against Omicron variants.1 The findings indicate that while high levels of vaccine-induced antibodies in the blood reduce viral load after infection occurs, specialized mucosal antibodies inside the nose provide the primary shield against becoming infected in the first place.1
How do nasal antibodies stop SARS-CoV-2 at the point of entry?
Nasal immunoglobulin A intercepts viral particles directly on the airway lining before the pathogen can penetrate epithelial cells. In the initial four-week screening investigation of 368 triple-vaccinated healthcare workers, who experienced an overall infection rate of 22 percent during the monitoring period, the thesis found that high serum antibody levels against the ancestral viral spike protein correlated with lower viral loads in infected participants.1 However, the thesis noted that the heightened protection observed in individuals with hybrid immunity, acquired through both vaccination and prior natural exposure, appeared to be mediated largely by mucosal spike-specific immunoglobulin A.1
A subsequent study tracking 337 of those healthcare workers confirmed the direct protective effect of mucosal immunity in the upper airway.1 Participants with baseline nasal spike immunoglobulin A concentrations above the 75th percentile had a 65 percent lower risk of Omicron infection compared with individuals whose nasal antibody levels fell below that threshold.1 When infections did occur, the research identified a clear temporal sequence in which rising levels of nasal antibodies coincided with declining viral loads, alongside a faster mucosal response among people who had recovered from an earlier infection.1
How long does mucosal protection against new variants persist?
Protective mucosal antibody levels in the nasal lining can endure for at least eight months after an infection.1 In the third investigation, participants whose nasal spike immunoglobulin A levels placed them above the 75th percentile at baseline maintained a significantly reduced infection risk over eight months of observation, recording a hazard ratio of 0.55 compared with participants below that baseline threshold.1 Mucosal durability was particularly pronounced among individuals who experienced repeat exposure: seven months after infection, 94 percent of reinfected participants and 58 percent of individuals recovering from their first infection still maintained nasal antibody levels exceeding the baseline 75th percentile mark.1
That localized mucosal barrier also remained effective when challenged by newer viral lineages. In the fourth study, which assessed exposure to emerging Omicron BQ strains, individuals with detectable nasal spike immunoglobulin A experienced an incidence rate ratio of 0.42 relative to those without detectable levels, indicating substantial protection.1 The thesis reported a linear association across the cohort, showing that as the concentration of nasal antibodies increased, the likelihood of contracting an infection dropped steadily.1
What can these findings tell us about future vaccine design?
These findings do not demonstrate that existing injected vaccines are ineffective, but rather that systemic and mucosal immune pathways perform distinct protective jobs. The research investigated observational cohorts of adult healthcare workers, meaning the measured outcomes reflect real-world exposure patterns in a specific occupational group rather than a controlled clinical trial. Furthermore, antibody measurements in nasal secretions serve as an indicator of mucosal defense, but they do not capture every element of cellular immunity operating inside airway tissues.
Recognizing the independent power of mucosal antibodies clarifies why preventing transmission requires a different immunological strategy than preventing hospital admission. While intramuscular injections excel at generating long-lasting systemic defenses in the blood, establishing a durable barrier against respiratory infection may ultimately require mucosal vaccines, such as nasal sprays, designed to stimulate protective immunoglobulin A directly along the lining of the respiratory tract.
What this rests on
13 sentences trace to 1 source.
-
1
TM
Teamwork makes the dream work : systemic and mucosal immunity in shaping protection against SARS-CoV-2 Document · oatd.org Teamwork makes the dream work : systemic and mucosal immunity in shaping protection against SARS-CoV-2. See the source